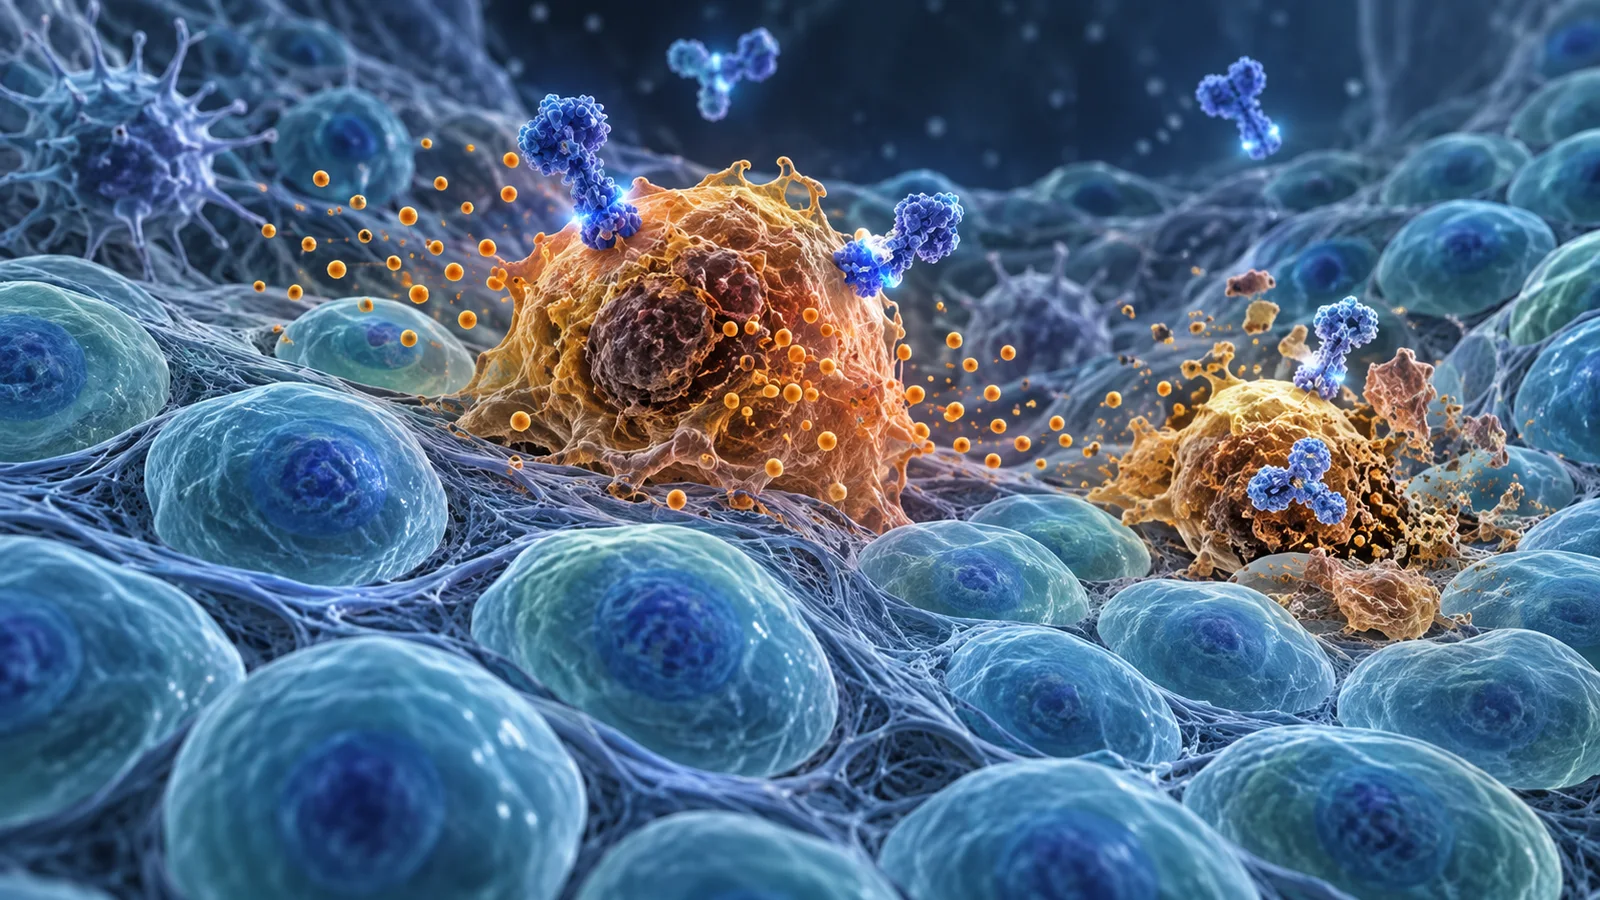
Senolytics: The Science of Clearing Zombie Cells
Explore senolytic drugs that clear senescent zombie cells, from dasatinib-quercetin to fisetin, and what clinical trials reveal about their potential.
Table of Contents
DISCLAIMER
This article is for informational purposes only and does not constitute medical advice. The statements in this article have not been evaluated by the FDA. The information presented is based on published research and should not be used as a substitute for professional medical guidance. Consult your physician before starting any supplement or health protocol.
A New Class of Anti-Aging Drugs
The discovery that senescent cells could be selectively eliminated, and that doing so could extend healthy lifespan and reverse aspects of aging in animal models, opened one of the most promising frontiers in geroscience. Senolytic drugs — compounds designed to clear these harmful zombie cells — represent the first pharmacological approach that directly targets a fundamental mechanism of aging rather than treating its downstream consequences one disease at a time.
Since the first senolytic drug combination was identified in 2015, the field has progressed rapidly from laboratory discovery to animal validation to human clinical trials. This article reviews the science behind senolytic drugs, the compounds under development, clinical trial results to date, and what the future may hold.
How Senolytics Work
The Achilles Heel of Senescent Cells
Senescent cells survive in tissues despite being damaged and dysfunctional because they upregulate specific anti-apoptotic (pro-survival) pathways. These survival networks are their Achilles heel — the vulnerability that senolytics exploit.
James Kirkland and colleagues at the Mayo Clinic used a bioinformatics approach to map these survival networks and identified several key pathways:
- BCL-2/BCL-XL family: Anti-apoptotic proteins that block programmed cell death
- PI3K/AKT pathway: A pro-survival signaling cascade
- Tyrosine kinase signaling: Growth factor-dependent survival
- p53/p21/serpine axis: Cell cycle regulators reconfigured for survival
- HIF-1alpha: Hypoxia-response pathways adapted for survival
By inhibiting one or more of these pathways, senolytic drugs tip the balance in senescent cells from survival toward apoptosis. Because healthy cells do not depend on these pathways to the same extent, they are largely spared.
The Hit-and-Run Approach
A critical insight about senolytic therapy is that it requires only intermittent dosing. Unlike drugs for chronic conditions that must be taken continuously, senolytics need only brief exposure to trigger senescent cell death. Once cleared, senescent cells take weeks to months to re-accumulate. This intermittent approach, typically 1-3 days of treatment followed by weeks off, minimizes side effects while maintaining efficacy.
Leading Senolytic Compounds
Dasatinib Plus Quercetin (D+Q)
Mechanism: Dasatinib is a multi-kinase inhibitor that targets senescent fat cell progenitors and cells dependent on tyrosine kinase signaling. Quercetin inhibits PI3K and BCL-2 family survival pathways, targeting senescent endothelial cells and bone marrow stem cells. Together they cover a broader range of senescent cell types.
Animal data: D+Q has shown remarkable results including 36% extension of remaining lifespan when given to old mice, improved physical function, reduced atherosclerosis, and better metabolic parameters.
Human trials:
- Idiopathic pulmonary fibrosis: Improved physical function (walk distance, chair stands) after three weeks
- Diabetic kidney disease: Reduced senescent cell markers in adipose tissue and skin, decreased SASP factors in blood
- Ongoing trials in Alzheimer’s disease, osteoarthritis, frailty, and other conditions
Dosing protocol (research): Typically 100mg dasatinib plus 1000mg quercetin daily for three consecutive days, repeated every 2-4 weeks.
Fisetin
Mechanism: A flavonoid found naturally in strawberries, apples, and grapes that targets multiple senescent cell survival pathways including BCL-2 family proteins and PI3K/AKT signaling.
Advantages: Natural compound with established dietary safety record, available as a supplement, potentially effective as a standalone senolytic.
Animal data: A 2018 study showed that fisetin extended median and maximum lifespan in aged mice when treatment was started late in life. Fisetin also reduced senescent cell markers in multiple tissues and improved tissue function.
Human trials: The AFFIRM trial at the Mayo Clinic is studying fisetin (20mg/kg for two consecutive days per month) in older adults to assess its effects on senescent cell burden and inflammatory markers. Additional trials are examining fisetin for COVID-19 complications, frailty, and osteoarthritis.
Accessibility: Available as an over-the-counter supplement, though senolytic dosing (high-dose, intermittent) differs from typical supplement use.
Navitoclax (ABT-263)
Mechanism: A potent and specific BCL-2/BCL-XL inhibitor originally developed as a cancer therapy.
Senolytic potency: Among the most potent senolytic compounds identified, effectively clearing senescent cells across multiple cell types.
Limitations: Causes significant thrombocytopenia (reduction in blood platelets) because platelets depend on BCL-XL for survival. This side effect limits its clinical utility for chronic senolytic therapy.
Modified approaches: Researchers are developing navitoclax prodrugs that are activated specifically within senescent cells, potentially preserving senolytic potency while reducing platelet toxicity.
Procyanidin C1 (PCC1)
A compound derived from grape seed extract identified as a senolytic in a 2021 study. PCC1 showed senolytic activity at higher concentrations while acting as a senomorphic (SASP suppressor) at lower concentrations. Its natural origin and dual mechanism make it an interesting candidate, though research is still in early stages.
UBX0101
Developed by Unity Biotechnology, UBX0101 is a p53/MDM2 interaction inhibitor designed as a locally injected senolytic for osteoarthritis. While it showed promise in animal models, a Phase 2 clinical trial in knee osteoarthritis patients did not meet its primary endpoint for pain reduction, representing an important setback for the field.
Clinical Trial Landscape
Completed and Ongoing Trials
As of 2026, senolytic clinical trials span multiple conditions:
| Compound | Condition | Status | Key Findings |
|---|---|---|---|
| D+Q | IPF | Published | Improved physical function |
| D+Q | Diabetic kidney disease | Published | Reduced senescent cells in tissue |
| D+Q | Alzheimer’s disease | Ongoing | Preliminary results pending |
| D+Q | Frailty | Ongoing | Safety data encouraging |
| Fisetin | Frailty (AFFIRM) | Ongoing | Primary outcomes pending |
| Fisetin | COVID complications | Ongoing | Preliminary data collecting |
| D+Q | Hematopoietic stem cell transplant | Ongoing | Safety focus |
What Trials Have Shown So Far
Encouraging findings:
- Senolytics can reduce senescent cell markers in human tissues
- Physical function improvements are measurable within weeks
- Intermittent dosing appears safe in the studied populations
- SASP markers decrease in blood, suggesting systemic anti-inflammatory effects
Limitations:
- Sample sizes have been small (typically 10-20 participants per arm)
- Follow-up periods have been short (weeks to months)
- No trial has yet demonstrated effects on hard endpoints like mortality or disease incidence
- The UBX0101 osteoarthritis failure highlights the gap between animal and human results
Challenges and Open Questions
Identifying Senescent Cells
One of the field’s biggest challenges is accurately measuring senescent cell burden in humans:
- No single biomarker uniquely identifies senescent cells
- p16, p21, SA-beta-galactosidase, and other markers are used but none is perfectly specific
- Blood-based SASP markers (IL-6, MCP-1, PAI-1) are indirect measures
- Tissue biopsy provides more direct assessment but is invasive
- Better biomarkers are needed to measure treatment response
Tissue-Specific Approaches
Different tissues harbor different types of senescent cells with different survival pathways:
- A senolytic effective in fat tissue may not work in the brain
- Tissue-specific delivery systems may be needed for some applications
- Local delivery (injection) avoids systemic exposure but limits treatment scope
Long-Term Safety
Questions about long-term senolytic safety include:
- Could chronic elimination of senescent cells impair wound healing or tumor suppression?
- Might sustained SASP reduction compromise beneficial immune surveillance?
- What are the effects of decades of intermittent senolytic use?
- Could resistance develop if senescent cells evolve alternative survival pathways?
Optimal Timing
When to start senolytic therapy is debated:
- Starting too early may remove beneficial senescent cells involved in tumor suppression
- Starting too late may mean too much damage has already accumulated
- The optimal age and frequency of treatment are unknown
The Self-Experimentation Question
Given that quercetin and fisetin are available as supplements, some individuals are self-experimenting with senolytic protocols outside of clinical trials. This raises important considerations:
Arguments for caution:
- Clinical trial data is still limited and preliminary
- The optimal dose, frequency, and combination for humans is not established
- Interactions with medications and health conditions are not fully characterized
- Self-monitoring of senescent cell burden is not possible
- The risk-benefit ratio for healthy individuals is unknown
What the compounds are: Both quercetin and fisetin are natural flavonoids with long dietary safety records. However, senolytic dosing protocols use much higher doses than dietary exposure, and long-term safety at these doses has not been established.
The Future of Senolytics
Next-Generation Approaches
Targeted prodrugs: Compounds that are inactive until they encounter senescent cell-specific enzymes (like SA-beta-galactosidase), achieving selective activation within senescent cells.
CAR-T cell therapy: Engineered immune cells targeting surface markers unique to senescent cells. This approach leverages the specificity of the immune system for potentially more selective clearance.
Gene therapy approaches: Using viral vectors to deliver suicide genes that are only activated in senescent cells.
Combination strategies: Pairing senolytics with other longevity interventions (NAD+ boosting, partial reprogramming, metabolic optimization) may produce synergistic benefits.
The Regulatory Pathway
A significant challenge for senolytics is the regulatory framework. Aging itself is not recognized as a disease by the FDA, so senolytic drugs must currently be developed for specific age-related conditions. If the TAME trial (testing metformin) establishes a precedent for aging as a treatable indication, it could accelerate the approval pathway for senolytics and other anti-aging therapies.
The Bottom Line
Evidence Ladder and a Practical Decision Rule
Senolytic evidence is strongest for a biological mechanism and selected animal models. Cell-culture experiments show that different senescent cell types depend on different survival pathways. Mouse studies show that clearing some of those cells can improve specific functions, but a compound that works in one tissue or disease model may fail in another. Early human studies and trial protocols establish feasibility and help define safety; they do not yet demonstrate longer life or broad rejuvenation in healthy adults. The 2026 fisetin literature also illustrates the gap: active clinical translation and randomized protocols exist, while definitive disease and longevity outcomes remain limited.
A practical reader test is to separate availability from evidence. Quercetin or fisetin being sold as supplements does not validate high-dose, intermittent “senolytic” regimens, and a prescription cancer drug being medically available does not make off-label combinations safe. Ask whether the exact compound, dose, population, and outcome were studied in humans; check whether platelet, liver, kidney, immune, and drug-interaction risks were monitored; and prefer registered trials over influencer protocols. For now, senolytics are a research field with credible hypotheses and unresolved clinical tradeoffs, not a self-care category.
Senescence Is a State, Not a Single Target
The phrase “senescent cell” can imply a uniform unwanted population, but senescence is heterogeneous. Cells enter the state after different stresses, use different survival pathways, and release different signaling molecules depending on tissue and time. Some senescent cells contribute to wound healing, development, and tumor suppression before immune clearance. The therapeutic goal is not necessarily to remove every cell carrying one marker; it is to reduce harmful, persistent populations without disrupting useful transient responses.
This heterogeneity explains why a compound can appear selective in one culture system and perform differently in another organ. It also complicates biomarkers. SA-beta-galactosidase activity, p16 expression, p21 signaling, and components of the senescence-associated secretory phenotype are informative but not uniquely definitive by themselves. Human trials need combinations of tissue, molecular, functional, and safety measurements rather than a single blood marker.
The first small human studies are valuable because they test feasibility and whether tissue markers move in the expected direction. They are not powered to show that intermittent clearance prevents dementia, cardiovascular disease, disability, or death. The 2026 fisetin review and randomized-trial protocol show that the field is still defining doses, populations, and endpoints. A protocol publication is evidence that a controlled study is planned; it is not a positive result.
The clearest path forward is disease- or tissue-specific. A senolytic may eventually help a defined condition in which persistent senescent cells have a demonstrated role, while offering no net benefit to a healthy person. That outcome would still be scientifically and clinically meaningful, even if the broad promise of a universal anti-aging purge proves unrealistic.
Senolytics represent one of the most scientifically grounded and rapidly advancing approaches to treating aging at its source. The progression from identifying senescent cell survival pathways (2015) to demonstrating lifespan extension in mice (2018) to first-in-human clinical trials (2019) has been remarkably fast by pharmaceutical development standards. While definitive proof of clinical benefit in humans awaits larger, longer trials, the preclinical evidence is compelling and the biological rationale is strong. As the clinical trial landscape matures over the coming years, senolytics may become one of the first true anti-aging therapies available to patients.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare professional before considering any senolytic protocol.
Frequently Asked Questions
What are senolytic drugs?
Are senolytic drugs available now?
How often do you need to take senolytic drugs?
Sources
- The Achilles' heel of senescent cells: from transcriptome to senolytic drugs(2015)
- Senolytics improve physical function and increase lifespan in old age(2018)
- Fisetin is a senotherapeutic that extends health and lifespan(2018)
- Senolytic drugs: from discovery to translation(2020)
- Clinical Translation of Fisetin for Age-Related Diseases: Current Evidence and Future Opportunities(2026)
- Low-Dose Fisetin Supplementation and Its Association With Chronic Inflammation in Middle-Aged and Older Adults: Study Protocol for a Triple-Blind, Randomised, Placebo-Controlled Trial(2026)
- Senolytics decrease senescent cells in humans: Preliminary report from a clinical trial of Dasatinib plus Quercetin in individuals with diabetic kidney disease(2019)
Stay Updated on Longevity Science
Weekly research digests. No spam, unsubscribe anytime.
Related Articles
Arterial Stiffness and Vascular Age: A Longevity Evidence Guide
Understand arterial stiffness vascular age longevity links, key studies, measurement limits, and evidence-based lifestyle implications for healthy aging.
11 min read
Arterial Stiffness and Vascular Aging: What the Evidence Shows
Explore arterial stiffness vascular aging, how vessels change over time, what pulse wave velocity studies show, and practical ways evidence may inform prevention.
10 min read
Autophagy and Aging: Your Body's Cellular Cleanup System
Explore autophagy, your body's cellular cleanup system, and its critical role in aging and longevity. Research suggests modulating autophagy may support cellular health.
12 min read