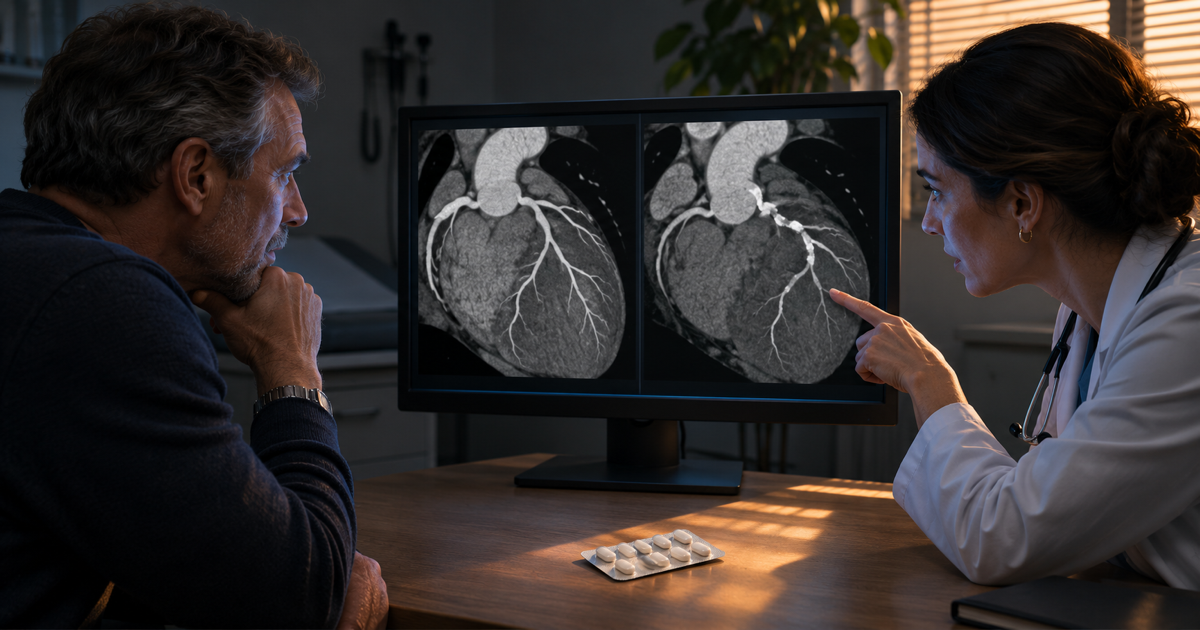
Pitavastatin May Cut Heart Events in HIV, With a Diabetes Trade-off
In the REPRIEVE trial, pitavastatin may have reduced major cardiovascular events in people with HIV on treatment, while new diabetes was more common.
Table of Contents
DISCLAIMER
This article is for informational purposes only and does not constitute medical advice. The statements in this article have not been evaluated by the FDA. The information presented is based on published research and should not be used as a substitute for professional medical guidance. Consult your physician before starting any supplement or health protocol.
On October 27, 2026, a U.S. HIV guidelines panel endorsed offering statins to people aged 40 to 75 on stable antiretroviral treatment, even when their LDL cholesterol or estimated cardiovascular risk would ordinarily put them below a treatment threshold. That update could change a midlife checkup for someone whose HIV is well controlled and whose earlier heart-risk estimate gave them little reason to discuss a statin. U.S. HIV cardiovascular guidelines
The evidence behind that change includes a trial called REPRIEVE, which assigned 7,769 people with HIV to pitavastatin or a placebo. Over a median 5.6 years, the pitavastatin group had fewer major cardiovascular events. The group also had more new diagnoses of diabetes and more severe or treatment-limiting muscle symptoms. The trial gives a clearer picture of which outcomes might change when people begin a statin before they develop known cardiovascular disease, and which trade-offs can accompany that decision. REPRIEVE trial update · U.S. HIV cardiovascular guidelines
Who was in the trial
REPRIEVE enrolled people aged 40 to 75 who were taking antiretroviral medication, had no known atherosclerotic cardiovascular disease and were classified as having low to moderate cardiovascular risk by conventional criteria. The median participant was 50. The study therefore examined a decision that can arise well before old age, when someone has had no heart attack or stroke and their HIV treatment is already established. Random assignment and a matched placebo helped the investigators estimate what adding pitavastatin might change, while both groups continued to receive HIV care. Original REPRIEVE report
That population matters because a cardiovascular risk score can miss some of the risk associated with HIV. Conventional scores use factors such as age, smoking, cholesterol and blood pressure. The 2026 HIV guidelines note that even the newer PREVENT equations may underestimate atherosclerotic cardiovascular risk in people with HIV, with particularly important underprediction in women. A risk estimate can still help describe someone’s underlying chances of an event. In this setting, it may be a less reliable gatekeeper for deciding when a conversation about statins should begin. U.S. HIV cardiovascular guidelines
The investigators tested pitavastatin in part because of its potential for relatively few interactions with antiretroviral drugs. That design choice made it possible to study cardiovascular risk on top of ongoing HIV treatment. It also limits what can be inferred about other statins. REPRIEVE directly compared one drug with a placebo, so it did not measure whether another statin would deliver the same balance of benefit and harm alongside a particular HIV regimen. Original REPRIEVE report · U.S. HIV cardiovascular guidelines
What the 36% estimate measures
At the end of the trial, investigators recorded an estimated 4.95 first major cardiovascular events per 1,000 person-years in the pitavastatin group and 7.77 in the placebo group. A person-year combines the number of people followed and the time they contributed. The difference was about 2.8 events per 1,000 person-years under trial conditions. The comparison over time gave a hazard ratio of 0.64, with a 95% confidence interval from 0.48 to 0.84. The point estimate corresponds to a 36% relative reduction in the hazard of a first event. REPRIEVE trial update
The absolute rates give the percentage its scale. When events are infrequent, a substantial relative reduction can correspond to a modest difference in the number of people who experience one over several years. Even if two people could expect the same proportional reduction, the person with the higher underlying cardiovascular risk would generally have more absolute risk to reduce. The trial’s average gives a sense of the benefit across the enrolled population. An individual’s chance of avoiding an event may differ from that average. REPRIEVE trial update · U.S. HIV cardiovascular guidelines
The main outcome included heart attack and stroke alongside other prespecified events, including cardiovascular death and procedures to restore arterial blood flow. Combining outcomes gave investigators more events with which to estimate the treatment effect. It also means that the 36% figure belongs to the combined outcome. An estimate for any one component, such as cardiovascular death, draws on fewer events and can carry more uncertainty. Original REPRIEVE report · REPRIEVE trial update
What two scans revealed about coronary plaque
A substudy at 31 U.S. research sites used coronary CT angiography to look inside the arteries that feed the heart. Participants were scanned near enrollment and again about two years later. The investigators focused on noncalcified plaque, deposits that CT can distinguish from densely calcified areas. Following plaque volume in the same person across two scans gave the team a way to examine what might change in the artery wall before enough clinical events occurred to compare the groups. REPRIEVE coronary imaging substudy
Among the 611 participants with paired scans, average noncalcified plaque volume fell by 1.7 cubic millimeters in the pitavastatin group and rose by 2.6 cubic millimeters in the placebo group. The baseline-adjusted difference was 4.3 cubic millimeters in favor of pitavastatin. The confidence interval extended from 0.1 to 8.6 cubic millimeters in that direction, leaving room for a small average effect. Plaque progression was also less frequent in the pitavastatin group, with an estimated relative risk of 0.67. Those averages describe a difference between groups whose individual scan results varied considerably. REPRIEVE coronary imaging substudy
The substudy found changes in several measurements that could help explain the imaging results. LDL cholesterol fell more with pitavastatin, as did oxidized LDL. An enzyme linked to inflammation in the artery wall, lipoprotein-associated phospholipase A2, also fell in the pitavastatin group while rising in the placebo group. Taken together, these findings are consistent with less accumulation of some forms of plaque and changes in processes that may affect the artery wall. Because treatment altered several measures together, the study could not isolate how much each change contributed to the reduction in clinical events. REPRIEVE coronary imaging substudy
The paired scans also came from a narrower population than the main trial. Of 804 people enrolled in the imaging study, 611 contributed both scans to the plaque analysis, and 84% of that group were men. The scan results may help explain how pitavastatin worked. The larger international trial remains the stronger basis for estimating the clinical benefit across people who met the enrollment criteria. REPRIEVE coronary imaging substudy · Original REPRIEVE report
The diabetes and muscle findings
The final follow-up found a higher rate of new diabetes in the pitavastatin group, with an incidence rate ratio of 1.29. The 95% confidence interval ran from 1.07 to 1.57. Severe or treatment-limiting muscle symptoms were also more frequent, with a rate ratio of 1.58 and a wider confidence interval of 1.14 to 2.19. Those estimates describe relative differences between the groups. A rate ratio of 1.29 corresponds to an estimated 29% higher rate of new diabetes during follow-up, while the absolute difference depends on how often diabetes occurred in the comparison group. U.S. HIV cardiovascular guidelines
The original report gives an earlier view in simple proportions. At a median 5.1 years, it recorded new diabetes in 5.3% of the pitavastatin group and 4.0% of the placebo group, a difference of 1.3 percentage points. It reported qualifying muscle symptoms in 2.3% and 1.4%, respectively. Those proportions come from the earlier cutoff and use a different scale from the final follow-up’s rate ratios. They give a rough sense of how common the outcomes were among participants during the first five years. Original REPRIEVE report
Comparing benefit and harm requires keeping track of what each outcome means to a person. A coronary procedure, a stroke, a diabetes diagnosis and muscle pain severe enough to interrupt treatment have different consequences. A reader interpreting the results for a clinical conversation may be better served by looking at their cardiovascular risk, their risk of diabetes and the potential for interactions with their HIV regimen separately. The trial lets those factors inform the discussion because it reported harms alongside the event reduction. Original REPRIEVE report · U.S. HIV cardiovascular guidelines
How far the findings reach
A separate REPRIEVE analysis looked at major illnesses outside cardiovascular disease. Over a median 5.6 years, it found 9.17 major noncardiovascular events per 1,000 person-years with pitavastatin and 9.90 with placebo. The hazard ratio was 0.92, with a 95% confidence interval of 0.76 to 1.13. The data were compatible with a modest reduction or increase in these events. Cancers that were outside the AIDS-defining category remained the leading cause of death in both trial groups. This analysis offers little basis for extending the heart finding to cancer or to major illnesses in general. REPRIEVE analysis of noncardiovascular outcomes
For healthy aging, the most concrete implication is that some people living with treated HIV may have a better chance of reaching later life without a first major cardiovascular event. REPRIEVE followed participants long enough to estimate that effect over several years, but it did not establish how many years of life a person might gain. Its eligibility criteria also leave uncertainty about how closely the results would apply to people older than 75, those outside the trial’s risk range and those whose HIV care is less stable. The October update is most directly relevant to the decision the trial was built around, which is whether to address cardiovascular risk earlier in the course of treated HIV. REPRIEVE trial update · U.S. HIV cardiovascular guidelines
Frequently asked questions
Could pitavastatin help if my LDL is already in range?
It may. REPRIEVE enrolled people with treated HIV at low to moderate estimated cardiovascular risk, including people whose LDL would not ordinarily prompt a statin discussion.
Did pitavastatin clear coronary plaque?
The imaging substudy suggests pitavastatin may slightly reduce average noncalcified plaque volume over two years. It did not establish that coronary arteries cleared.
Did REPRIEVE show that pitavastatin adds years of life?
No. The trial suggests a reduction in first major cardiovascular events over several years. It did not establish a gain in life expectancy.
This article summarises published research and is not medical advice. Consult your healthcare provider before changing your routine.
Frequently Asked Questions
Could pitavastatin help if my LDL is already in range?
Did pitavastatin clear coronary plaque?
Did REPRIEVE show that pitavastatin adds years of life?
Sources
- U.S. HIV guidelines on cardiovascular and metabolic complications, October 2026(2026)
- Pitavastatin to Prevent Cardiovascular Disease in HIV Infection(2026)
- Trial Update of Pitavastatin to Prevent Cardiovascular Events in HIV Infection(2026)
- REPRIEVE Mechanistic Substudy of Coronary Plaque and Inflammatory Biomarkers(2026)
- REPRIEVE Analysis of Major Noncardiovascular Events(2026)
Stay Updated on Longevity Science
Weekly research digests. No spam, unsubscribe anytime.
Related Articles
Arterial Stiffness and Vascular Age: A Longevity Evidence Guide
Understand arterial stiffness vascular age longevity links, key studies, measurement limits, and evidence-based lifestyle implications for healthy aging.
11 min read
Arterial Stiffness and Vascular Aging: What the Evidence Shows
Explore arterial stiffness vascular aging, how vessels change over time, what pulse wave velocity studies show, and practical ways evidence may inform prevention.
10 min read
Aspirin May Increase Bleeding Without Extending Disability-Free Life
In older adults without cardiovascular disease, aspirin trials suggest bleeding risks may outweigh preventive benefits, with no demonstrated gain in independent life.
8 min read